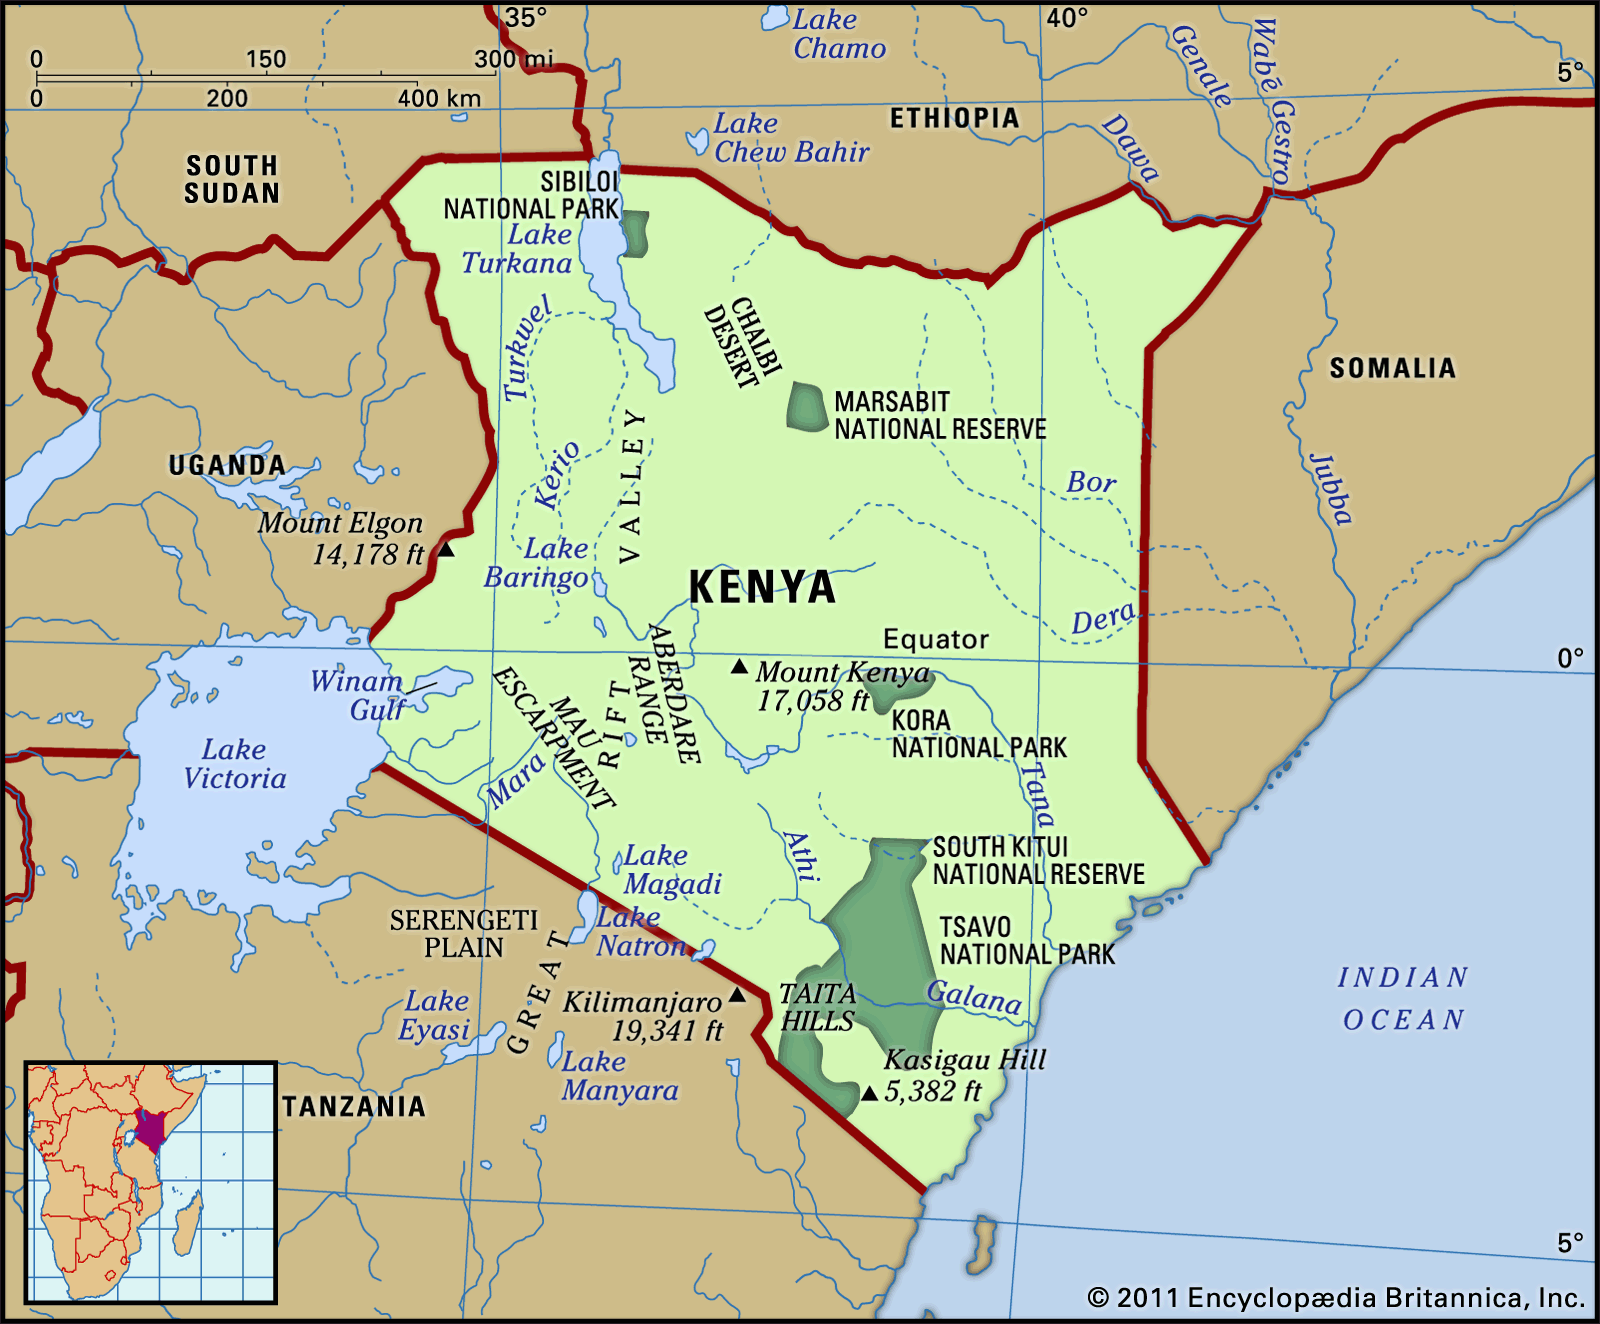
Borders on paper mean very little to a virus. When Kenyan health authorities confirmed the country's first-ever case of Ebola, it wasn't just a grim milestone for Nairobi; it was the inevitable collision between a raging regional epidemic and modern transit networks. A Kenyan citizen living in the Democratic Republic of Congo traveled by road to Kampala before catching a commercial Jambojet flight to Nairobi. He arrived over the weekend, sought care at a private hospital, and tragically died. Now, public health officials are racing against the clock to trace dozens of passengers and contacts.
If you think this single imported case is an isolated incident, you don't understand how cross-border trade and regional migration operate in East Africa.
The Anatomy of an Imported Outbreak
The Democratic Republic of Congo has been locked in a brutal battle with its largest-ever recorded Ebola outbreak. We are talking about an epidemic that has infected over 8,000 people and claimed upwards of 4,000 lives. It is driven by the rare Bundibugyo strain, a vicious variant that complicates traditional containment efforts because it lacks a widely proven commercial vaccine or specific standard treatment.
When the infected traveler landed in Nairobi, he managed to slip past standard entry screenings. Why? Health officials noted that medication likely masked his early symptoms, allowing him to board a commercial flight undetected. This highlights a terrifying weak point in modern epidemiological surveillance: thermal scanners and questionnaire checkpoints at airports cannot catch someone whose symptoms are artificially suppressed by fever reducers or early-stage obscurity.
You can't rely solely on perimeter defense. Viruses find the cracks in the armor every single time.
Why Contact Tracing Is Testing Nairobi's Limits
The immediate reaction from Kenyan Health Minister Aden Duale was swift: authorities announced they had identified 28 local contacts and were actively tracking down 27 other passengers from the same flight. These individuals face mandatory 21-day isolation protocols, the standard incubation window for the filovirus.
Running contact tracing in a bustling metropolis like Nairobi is an administrative nightmare compared to rural containment zones. People move constantly across neighborhoods, use multiple mobile payment platforms, and ride packed minibuses known as matatus. Tracking down a plane full of passengers who have already dispersed into a city of over four million people demands absolute precision and immense public cooperation.
Kenya claims to be prepared, having trained nearly 5,000 health workers across the country since the DRC outbreak began heating up. Yet, theory and practice look entirely different when a patient walks into a private city hospital presenting with chills, fever, and subtle signs of internal bleeding before doctors realize what they are dealing with.
The Broader Regional Threat
This case pulls the curtain back on a broader systemic crisis. The World Health Organization has watched the DRC outbreak swell, warning that it threatens to rival some of the worst historical epidemics in West Africa. When a country's public health infrastructure is strained by continuous conflict, economic instability, and community mistrust, containment turns into an exhausting game of whack-a-mole.
Neighboring nations like Uganda, Rwanda, and Kenya live on perpetual high alert because commercial and familial ties bind these borders tightly together. People cross daily for work, school, and commerce. Closing borders completely is economically impossible, meaning regional cooperation and transparent data sharing are the only real shields available.
If local clinics don't immediately isolate patients presenting with malaria-like symptoms that fail to respond to standard treatments, the window for containment slams shut in days.
What Comes Next For Public Health
Panic is entirely useless here, but blind complacency is fatal. The next three weeks will dictate whether Nairobi successfully boxed in this transmission chain or if secondary cases begin to emerge. Health ministries across East Africa must overhaul screening protocols to look beyond simple temperature checks, focusing instead on deep travel histories and active symptom screening.
Watch the quarantine numbers over the coming fortnight. If those isolated contacts test negative and clear the 21-day mark without developing symptoms, Kenya will have dodged a massive bullet. If a single second-generation case slips through the cracks, the playbook changes overnight. Keep your eyes on the data, ignore the sensationalist panic on social media, and watch how local public health systems handle the pressure.


